Constipation causes agitation in dementia because pain, pressure and discomfort build up when the person cannot explain what is wrong. Prevention rests on enough fibre and fluid, daily movement, and a calm, regular toileting routine. Agitation means restlessness, pacing, repetitive movements, calling out, irritability or disturbed sleep. In moderate dementia it affects 40–60% of people at some point, often because an internal stressor goes uncommunicated, according to dementia.co.uk in its guide to agitation and aggression.
Medical information disclaimer: This article is for general educational purposes only and does not provide medical advice, diagnosis, or treatment. Always consult a physician or other qualified health professional about symptoms, medications, tests, or treatment decisions.
Table of Contents
- Why does constipation get missed?
- How does bowel trouble affect comfort and continence?
- What should they eat and drink?
- What daily routine keeps bowels moving?
- What did a 2025 review find works best?
Why does constipation get missed?
Carers can easily miss constipation in an older person or someone with dementia. The NHS warns that behaviour changes such as confusion can signal pain or discomfort from constipation, in its constipation guidance. The person may not feel the urge clearly, remember the last bowel movement, or find words for bloating and cramping.
What a carer sees is instead new restlessness, refusal of care, poor sleep or sudden irritability. A useful check is PINCH-ME: pain, infection, nutrition and dehydration, constipation, hydration, medication and environment. Dementia guidance recommends this structured search for reversible causes before using medication for agitation.
How does bowel trouble affect comfort and continence?
Hard, impacted stool stretches the bowel and makes sitting, walking and sleeping uncomfortable. That constant pressure can raise distress in someone who already struggles to process bodily signals. Constipation also makes bladder emptying and control harder.
The Alzheimer's Society states that constipation is uncomfortable, affects bladder control, and is a very common cause of faecal incontinence when liquid stool flows around hard impacted stool, in its guide to toilet problems and continence. Soiling after days without a proper bowel movement often points to impaction with overflow, not diarrhoea. Treating the blockage matters more than restricting food or fluids.
What should they eat and drink?
Fibre adds bulk and fluids keep that bulk soft enough to pass. The NHS advises gradually increasing fibre, eating sorbitol-containing fruits such as apples, apricots, grapes, raspberries and strawberries, adding wheat bran, oats or linseed, drinking plenty of water and avoiding alcohol.
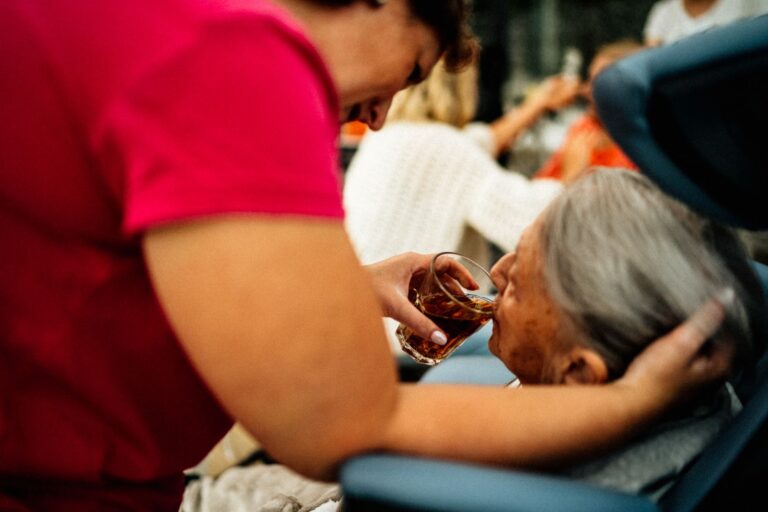
Fibre cannot work without fluid. Oxford Health NHS Foundation Trust explains that fibre acts like a sponge absorbing water, so without 1.5–2 litres daily intake stools stay hard, a particular risk when frail people cannot drink more. Small, steady habits help: offer water with every meal and medication round, keep a cup within reach, add vegetables and pulses across the week, and change laxatives or other medicines only with a clinician or pharmacist.
What daily routine keeps bowels moving?
A regular time and place helps the bowel learn when to empty. Give the person unhurried toilet time, respond promptly to urges, and build toileting into the dementia daily routine.
Position and movement matter too. Use a low footstool to raise knees above hips, encourage a short daily walk, and keep night-time trips safe and well lit.
- Keep the same toilet time each day, usually after breakfast
- Allow enough time and privacy without rushing
- Offer a footstool and steady handholds
- Record bowel movements, appetite, fluids and pain signs
- Ask a nurse, GP or pharmacist about new constipation, bleeding, vomiting or sudden agitation
What did a 2025 review find works best?
A 2025 scoping review on preventing constipation in people living with dementia found best-practice strategies were adequate dietary fibre and fluids, probiotics, individualized scheduled toileting, exercise, and staff education on bowel health. Home carers can borrow the same pattern: food, drink, timing, movement and shared notes.
Education is practical, not abstract. When everyone knows what normal looks like for that person, a two- or three-day gap, smaller stools, straining or new agitation triggers action rather than waiting.