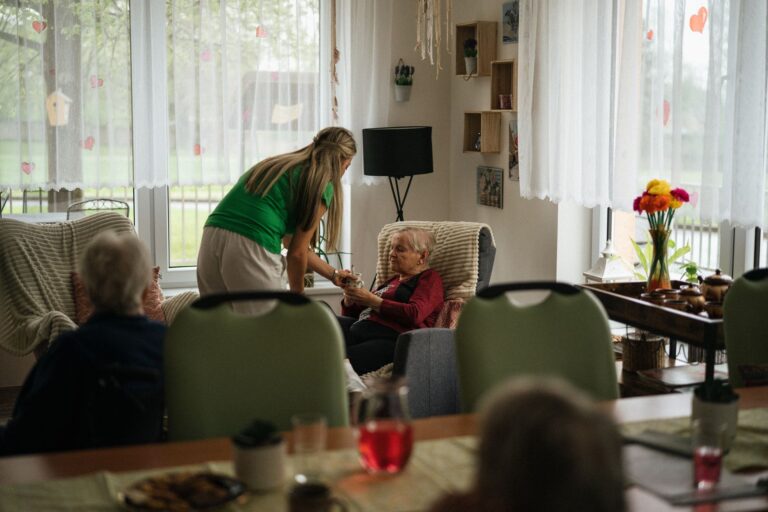Food pocketing in dementia is holding food or liquid in the cheeks or under the tongue without swallowing. Moving home from hospital means changing the eating space to support upright, calm meals and changing the care plan to keep prescribed textures, pacing, and mouth checks. East Sussex Healthcare NHS Trust describes pocketing as difficulty forming or clearing a bolus to trigger a swallow in its swallowing difficulties and dementia guide. Hospital discharge papers should carry that swallowing plan into home care, so caregivers continue the same textures without making changes alone.
Medical information disclaimer: This article is for general educational purposes only and does not provide medical advice, diagnosis, or treatment. Always consult a physician or other qualified health professional about symptoms, medications, tests, or treatment decisions.
Table of Contents
- Why is pocketed food risky at home?
- What does the swallowing assessment decide?
- How should the eating space change?
- How do you keep the hospital plan going?
Why is pocketed food risky at home?
Pocketed residue can slip toward the throat during breathing. Risk rises when the person reclines or is moved to bed after eating. Buckinghamshire Healthcare NHS Trust warns in its Swallowing Matters guide for care staff that this slip can cause choking, aspiration into the lungs, and aspiration pneumonia. Watch for coughing or choking during or after meals, gurgly voice, food left in the mouth, and prolonged chewing.
The Royal Orthopaedic Hospital NHS Trust also lists breathlessness, repeated chest infections, and weight loss as dysphagia signs. A new cough, wet voice, longer meals, or uneaten mouthfuls should prompt a call to the care team. Stay upright for a while after meals. Avoid giving food in bed, in a reclined chair, or right before a transfer.
What does the swallowing assessment decide?
A speech and language therapist assesses swallowing by watching eating and drinking, feeling throat movement, and listening to breathing. The Royal Orthopaedic Hospital NHS Trust says the therapist then prescribes diet or fluid changes, postures, or exercises, with dietitian support. The result is practical, not general.
It names which textures are safe, how thick drinks should be, what posture to use, and whether exercises apply. It also sets what to monitor, such as cough, voice change, or weight loss. Bring that written plan home from discharge. If no written texture or fluid plan arrived, ask the hospital team or family doctor for it before the next meal.
How should the eating space change?
Set one steady place for meals. Use a chair with back support and foot support, with hips and head upright. Turn off television, set phones aside, and keep conversation light so attention stays on swallowing.
East Sussex Healthcare NHS Trust recommends sitting fully upright and supported, with small bites and sips, slow pace, low distraction, and mouth checks in its swallowing difficulties and dementia guide. Use this routine: Look inside the cheeks and under the tongue. Prompt one more swallow if residue remains. Keep utensils small and cups light to slow intake.
- sit fully upright and supported through the meal
- offer one small bite or sip at a time
- keep a slow pace and pause between mouthfuls
- reduce noise and visual distraction
- check the mouth for leftover food after each swallow
How do you keep the hospital plan going?
Hospital discharge summaries carry the swallowing plan into the home care plan. Buckinghamshire Healthcare NHS Trust states in its Swallowing Matters guide for care staff that caregivers must continue the listed food textures and drink thickness without independent changes. The International Dysphagia Diet Standardisation Initiative standardizes those prescriptions as levels 0-7, with drinks at levels 0-4 and foods at levels 3-7. Match both thickness and particle size at home.
Do not thin a thickened drink or soften a diet further on your own. Careful hand feeding is the usual approach in advanced dementia. The American Geriatrics Society position, reviewed in the Journal of Clinical Medicine collection, finds equivalent outcomes for death, aspiration pneumonia, function, and comfort versus feeding tubes, with fewer restraints and tube problems. Ask the speech and language therapist for review if coughing, chest infections, or weight loss appear.