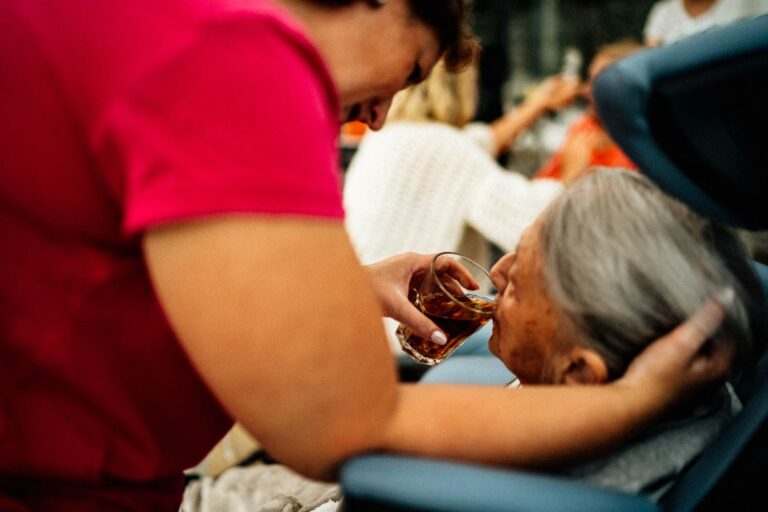
Food pocketing in memory care means holding food or medicine in the cheeks without swallowing. A safe plan uses upright seating, small bites, swallow checks, suitable textures, and prompt clinical review for warning signs.
East Sussex Healthcare NHS Trust links pocketing to impaired chewing, tongue movement, and poor swallow initiation its swallowing difficulties guidance. Those changes raise risk of choking, malnutrition, and aspiration pneumonia. Quick response protects eating safety and comfort.
Medical information disclaimer: This article is for general educational purposes only and does not provide medical advice, diagnosis, or treatment. Always consult a physician or other qualified health professional about symptoms, medications, tests, or treatment decisions.
Table of Contents
- Get a swallow assessment first
- How should you set up each meal?
- How do you pace each bite?
- Which foods and drinks are easier to manage?
- When should you seek prompt review?
Get a swallow assessment first
East Sussex Healthcare NHS Trust recommends referral to a speech and language therapist for a swallowing assessment. The therapist checks swallow safety in the person's usual eating setup. The visit sets the base for safer food choices.
The therapist then recommends textures, mealtime strategies, and next tests. Closer inspection may use instrumental testing such as FEES when needed. Use those results to guide every later step.
How should you set up each meal?
The Alzheimer's Association advises seating the person fully upright at about 90 degrees with head slightly forward its Food and Eating guidance. Move the head forward if it tilts back. Never feed someone drowsy, lying down, or reclined.
The National Institute on Aging advises staying upright during the meal and for at least 20–30 minutes afterward its late-stage Alzheimer's care guidance. This posture aids digestion and limits residue shifting toward the airway. The Alzheimer's Association tip sheet also advises calm, unhurried meals with minimal distractions and ample time, since late-stage meals may take an hour or longer.
How do you pace each bite?
The National Institute on Aging advises small bites and sips with a pause to confirm each swallow. Give a short "swallow" cue and a gentle downward neck stroke when needed.
Then visually check the cheeks and under the tongue for residue. Use the same order for every spoonful to reduce rushing and residue:.
- offer one small bite or sip
- wait and confirm the swallow
- cue again and recheck the mouth
- give more food only when the mouth is clear
Which foods and drinks are easier to manage?
The International Dysphagia Diet Standardisation Initiative describes softer, moist, bite-sized foods and clinician-prescribed drink thicknesses for unsafe swallows. Its IDDSI framework has eight levels, from Level 0 thin liquids to Level 7 regular foods. Match daily meals to the level the clinician prescribes.
Ask the speech and language therapist which level fits current chewing and swallow safety. Keep bites small and moist within that level. Change the level only after clinical review.
When should you seek prompt review?
Somerset NHS Foundation Trust advises checking the mouth after eating and maintaining oral hygiene. Texture changes alone do not eliminate aspiration risk.
Ongoing watch matters even when meals look smoother. Seek prompt clinical review for these warning signs: Bring notes on foods, seating, and timing to the visit.
- persistent coughing during or after meals
- chest infections, weight loss, or ongoing pocketing
- voice or breathing changes around eating