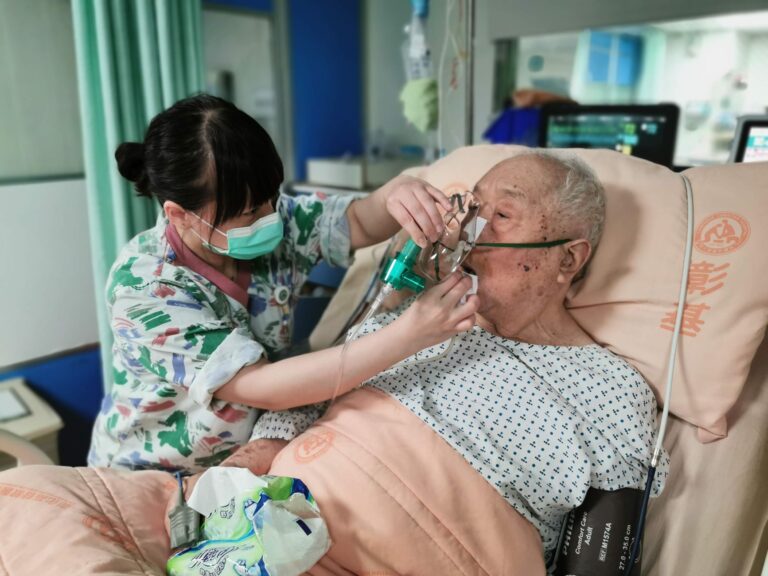
WHO is developing its first global guideline on prevention, diagnosis and management of delirium in older adults, explicitly including medication safety and deprescribing. For people with mild cognitive impairment (MCI), a stage of noticeable memory or thinking change that does not yet block daily life, the message is direct: review sedating medicines now because MCI sharply raises delirium risk. Delirium means sudden confusion, inattention and changed awareness, often triggered by acute illness or hospitalization. The World Health Organization describes it as common, serious and often preventable in older adults, yet under-recognized and under-treated.
Medical information disclaimer: This article is for general educational purposes only and does not provide medical advice, diagnosis, or treatment. Always consult a physician or other qualified health professional about symptoms, medications, tests, or treatment decisions.
Table of Contents
- Why MCI and delirium raise each other's risk
- Which medicines deserve a closer look?
- What does deprescribing actually mean?
- What can families do before the WHO guideline arrives?
- Frequently Asked Questions
Why MCI and delirium raise each other's risk
Pre-existing cognitive impairment is a principal risk factor that greatly increases likelihood of delirium during acute illness or hospitalization, according to a Maturitas review. That puts people with MCI in a high-alert group when they face surgery, infection, dehydration or a hospital stay.
Risk also runs the other way. MCI affects an estimated 6.7–25.2% of older adults as a transitional stage to dementia, while delirium itself is an independent risk factor for later dementia, according to the BMC Geriatrics MDDCohort protocol from November 2024. Preventing delirium therefore matters for both short-term recovery and long-term brain health.
Which medicines deserve a closer look?
The 2023 American Geriatrics Society Beers Criteria advise avoiding or minimizing anticholinergics, benzodiazepines, antipsychotics and Z-drugs in older adults because combined use raises risk of cognitive decline, delirium, falls and fractures, as reported in the 2023 Beers Criteria update. Examples include certain allergy, bladder, sleep and anxiety drugs, especially when taken together.
Cognitively vulnerable older people have heightened susceptibility to sedatives and anticholinergics that cause drowsiness, confusion and delirium, according to the validated STOPPCog tool published in Age and Ageing. The tool lists 23 deprescribing criteria for this group, giving clinicians a practical checklist beyond general age-based warnings.
What does deprescribing actually mean?
Deprescribing means carefully reducing or stopping a drug whose harms likely outweigh its benefits, with monitoring and gradual tapering when needed. It is not abrupt withdrawal and it is not simply going without treatment.
A 2026 nationwide U.S. cohort of adults 65 and older found new trazodone prescribing after delirium linked to safer outcomes than atypical antipsychotics, as reported by Lancet Healthy Longevity coverage. The finding suggests a potentially safer option when a drug cannot be avoided, but it does not make any sedative risk-free.
What can families do before the WHO guideline arrives?
The WHO guideline is still in development with evidence reviews underway, and much deprescribing support remains observational or consensus-based, according to the WHO methodologist notice. Readers do not need to wait for final wording to act on medication burden. An Irish Pharmacy Union review of sedative and anticholinergic burden points to the same practical steps for MCI: request regular medication reviews using Beers Criteria or anticholinergic-burden scales, taper high-risk sedatives gradually, and use non-drug delirium prevention first.
- Bring every prescription, over-the-counter drug, sleep aid and supplement to each review
- Ask which drugs are anticholinergic or sedating and whether dose, timing or alternatives can lower burden
- Plan any taper with the prescriber and pharmacist, with a clear follow-up date
- Pair changes with sleep routines, daytime activity, hydration, vision and hearing aids, and familiar orientation cues during illness or hospital stays
Frequently Asked Questions
Should a person with MCI stop sleep or anxiety medicines to prevent delirium?
Do not stop on your own. List all sedating drugs, ask for a review using Beers Criteria or an anticholinergic-burden scale, and taper only with medical supervision.
What helps most during hospitalization?
Keep orientation steady with glasses, hearing aids, daylight, fluids, movement and familiar presence, alongside the agreed medication plan.
You Might Also Like
- Safety Questions After the 2026 LiBBY Dementia Trial: How People With Mild Cognitive Impairment Can Avoid Overreading the Headline
- AAIC 2026 Findings on Retired Elite Soccer Players: How People With Mild Cognitive Impairment Can Avoid Overreading the Headline
- Repetitive Heading and Brain Health Findings at AAIC 2026: How People With Mild Cognitive Impairment Can Avoid Overreading the Headline