Reviewed by the Help Dementia Editorial Team — our editors review every article for accuracy against guidance from the National Institute on Aging, the Alzheimer’s Association, and peer-reviewed sources.
Dementia changes how the brain controls appetite and swallowing, often causing people to eat less, forget to eat, or struggle to swallow safely. These changes happen because the disease damages the parts of the brain responsible for hunger signals, taste perception, and the automatic coordination needed to move food from the mouth to the stomach. For example, a person with mid-stage dementia might sit in front of a full plate of their favorite meal and show no interest in eating, not because the food is unappealing, but because their brain no longer sends the signal that they are hungry.
These appetite and swallowing changes are among the most challenging aspects of dementia care because they affect nutrition, hydration, and overall health. When someone can’t swallow safely, they risk aspiration—food or liquid entering the lungs instead of going down the esophagus—which can lead to pneumonia and serious infections. Understanding what’s happening in the brain helps caregivers respond with patience and practical strategies rather than frustration.
Table of Contents
- Why Does Dementia Cause Loss of Appetite?
- How Swallowing Becomes Difficult and Dangerous
- How Taste, Smell, and Food Preferences Change
- Weight Loss and Nutritional Decline in Dementia
- Behavioral Changes Around Food and Mealtimes
- When to Consider Modified Diets and Feeding Assistance
- Long-Term Planning and Quality of Life Considerations
- Conclusion
- Frequently Asked Questions
Why Does Dementia Cause Loss of Appetite?
The hypothalamus, a small structure deep in the brain, controls hunger and satiety signals. As dementia progresses, this region deteriorates, breaking the communication between the body’s signals and the brain’s interpretation of those signals. A person might feel full immediately after taking a few bites, or not feel hungry at all even if they haven’t eaten in hours. Additionally, changes in taste and smell—also controlled by the brain—can make food taste metallic, bland, or unpleasant, which further reduces interest in eating. Memory loss compounds these problems.
People with dementia may not remember if they just ate, so they might refuse food minutes after finishing a meal, believing they haven’t been fed. Alternatively, someone might forget the purpose of sitting at the table and become agitated or confused about why food is in front of them. Compare this to typical aging, where appetite naturally decreases somewhat but the person still remembers recent meals and can communicate their preferences. Depression, which often accompanies dementia, also suppresses appetite. A person with dementia may withdraw from meals because of apathy or low mood, not because of physical inability to eat. This makes the situation more complex—it’s not purely a brain damage issue, but also an emotional one.

How Swallowing Becomes Difficult and Dangerous
swallowing is an automatic process involving dozens of muscles and precise timing coordinated by multiple brain regions. Dementia disrupts this coordination, leading to dysphagia (difficulty swallowing). In early stages, a person might choke slightly on liquids or have trouble with certain textures. As the disease progresses, they may have difficulty coordinating the tongue and throat muscles, leading to food being held in the mouth or swallowed at the wrong time. The most serious risk is silent aspiration, where food or liquid enters the airway without the person coughing or showing obvious signs of choking.
This is dangerous because aspirated material can lodge in the lungs, causing aspiration pneumonia, which can be life-threatening. A person with advanced dementia may not cough in response to aspiration because the reflex itself is damaged. This is why some people with dementia who appear to be eating normally may actually be having dangerous swallowing events that go unnoticed. Early warning signs include coughing during or after meals, wet-sounding voice (as if they’ve been crying), food residue around the mouth, or difficulty moving food from front to back of the mouth. If you notice these signs, it’s essential to have a swallow evaluation by a speech-language pathologist rather than waiting to see if the problem improves on its own. Ignoring swallowing problems can rapidly lead to malnutrition, dehydration, and serious infection.
How Taste, Smell, and Food Preferences Change
The brain’s taste and smell centers are particularly vulnerable to dementia. Someone who loved spicy food might find it burns their mouth unbearably, while another person might not taste anything at all because of olfactory nerve damage. This sensory loss is why many people with dementia reject foods they previously enjoyed and show interest only in very strong flavors—they’re seeking the taste sensation they can still perceive. Texture preferences often shift dramatically. A person who always ate regular solid foods may suddenly refuse anything chunky and only want soft, pureed items.
Or the opposite happens: someone with advanced dementia might prefer crunchy foods because they provide more tactile feedback, even if these foods are harder to swallow safely. Many caregivers discover through trial and error that their loved one with dementia will eat foods in specific forms but refuse the same food in another form—yogurt, for instance, when pureed with fruit might be accepted when similar foods in chunks are rejected. Temperature sensitivity also changes. Some people with dementia become extremely sensitive to hot foods and prefer everything at room temperature or cold. This can be an advantage for safety, since cooler foods give the throat more time to register the swallow reflex, but it limits the variety of meals that might otherwise appeal to them.

Weight Loss and Nutritional Decline in Dementia
Unintentional weight loss is one of the earliest and most visible signs that appetite and eating patterns are changing in dementia. A person might lose ten to twenty pounds over several months without trying, which strains the body and weakens immunity. The challenge for caregivers is distinguishing between the weight loss that’s unavoidable and the weight loss that could be slowed with better strategies. Compare two scenarios: In one, a person with early dementia simply forgets to eat lunch regularly. By changing the environment—setting a place at the table, sitting with them, or using visual cues like a plate of food—many caregivers can increase intake significantly. In another scenario, a person with advanced dementia has such severe swallowing dysfunction and food aversion that even with optimal support, they’re eating far less than before.
In this case, the focus shifts from trying to reverse weight loss to ensuring comfort and quality of life. These are very different problems requiring different solutions, but they both present as weight loss. Nutritional deficiencies from reduced intake can accelerate cognitive decline and physical frailty. The body needs protein to maintain muscle, and dementia patients already face natural muscle loss with age. When they eat less protein-rich food, they lose muscle faster, become weaker, and are more vulnerable to falls and infections. This creates a downward spiral that’s difficult to reverse.
Behavioral Changes Around Food and Mealtimes
As dementia progresses, mealtimes can become sources of confusion and conflict rather than nourishment. Some people become aggressive or agitated when presented with food, while others become suspicious about whether the food is safe to eat, sometimes refusing even when clearly hungry. These behavioral changes stem from the brain’s struggle to interpret sensory input and recognize familiar routines. One common but often misunderstood issue is overeating in earlier dementia stages. A person might eat everything on their plate and then ask for more immediately, or raid the kitchen for snacks every few minutes, because the satiety signals aren’t working.
They feel hungry even when they’ve just eaten. This is particularly challenging because caregivers must balance respecting the person’s apparent desires with preventing discomfort from overeating. Unlike the person who stops eating too much, this person needs portion control, but control that doesn’t feel like restriction or punishment. Mealtimes can also become distressing if the setting is chaotic or if the person feels rushed. A quiet environment, familiar foods, and allowing extra time can sometimes improve intake significantly. However, this requires consistent caregiver presence and patience, which isn’t always possible, especially in group care settings.

When to Consider Modified Diets and Feeding Assistance
Speech-language pathologists can recommend specific diet modifications—thickened liquids, pureed or minced textures, or specific food combinations—based on swallowing ability. These modifications can make eating safer and sometimes more enjoyable. However, modified diets have a tradeoff: they often taste worse and feel less satisfying than regular food, which can paradoxically reduce overall intake if someone is already struggling with appetite.
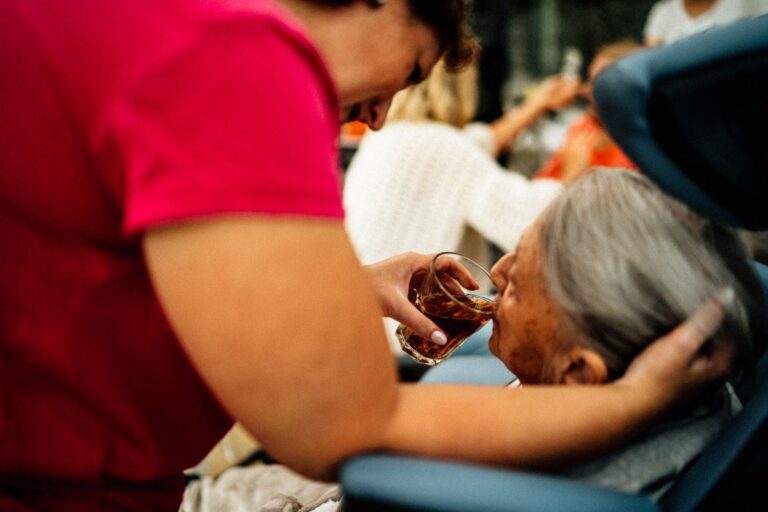
Some people benefit from feeding assistance—having a caregiver help guide food to the mouth or cut food into smaller pieces. This can increase intake and reduce anxiety during meals. In contrast, other individuals become distressed by help and refuse to eat when someone is feeding them, preferring independence even if it means eating less. Trial and observation are necessary to figure out what works for each person.
Long-Term Planning and Quality of Life Considerations
As dementia advances, questions about feeding tubes and artificial nutrition often arise. Some families pursue feeding tubes (such as percutaneous endoscopic gastrostomy, or PEG tubes) to ensure nutrition and hydration. Research shows that feeding tubes don’t actually extend life or prevent aspiration pneumonia in advanced dementia—the tube bypasses the mouth but the lungs are still at risk if the person aspirates saliva. Feeding tubes also come with their own risks: infection, displacement, and discomfort.
These are important factors to discuss with healthcare providers and loved ones when making decisions about artificial feeding. The shift in modern dementia care is toward comfort-focused approaches rather than aggressive nutritional interventions in advanced stages. This means focusing on foods the person enjoys, allowing them to eat as much or as little as they want, and prioritizing dignity and pleasure over calorie counts. This doesn’t mean neglecting nutrition entirely, but rather accepting that the goals change as the disease progresses.
Conclusion
Appetite and swallowing changes in dementia are complex problems rooted in brain degeneration, not stubbornness or simple picky eating. These changes affect not just nutrition but also safety, dignity, and the emotional experience of mealtimes for both the person with dementia and their caregivers. Understanding the why behind these changes—damaged hunger signals, altered taste, disrupted swallowing reflexes—helps caregivers respond with strategies tailored to the individual rather than generic approaches.
The most important step is early detection and evaluation. If you notice significant changes in eating, weight loss, or signs of swallowing difficulty, consult a healthcare provider or speech-language pathologist. They can identify specific problems and recommend practical modifications that work for your loved one. Throughout the dementia journey, flexibility and compassion—combined with professional guidance—offer the best path forward.
Frequently Asked Questions
Can someone with dementia aspirate without coughing?
Yes. Silent aspiration occurs when food or liquid enters the lungs without triggering a cough reflex. This is especially common in advanced dementia when the protective reflexes are damaged. It’s dangerous because the person and caregivers may not realize it’s happening until an infection develops.
Should we use feeding tubes if someone with dementia stops eating?
Research shows feeding tubes don’t extend life or prevent aspiration pneumonia in advanced dementia, and they carry their own risks and discomforts. This decision should involve your loved one’s healthcare team and family discussions about goals of care, weighing benefits and burdens.
Why does my relative with dementia want to eat things that aren’t food?
This behavior, called pica, occurs when dementia damages the brain’s ability to recognize what’s edible. It’s a safety concern requiring supervision and environmental management—removing non-food items that might be mistaken for food.
Is weight loss from dementia always unavoidable?
No. Some weight loss can be slowed with strategies like setting regular eating routines, offering favorite foods, eating together, and adjusting textures. However, in advanced dementia, some weight loss is part of the disease process despite best efforts.
How can I tell if my loved one prefers a modified texture?
Observe what they eat willingly and what they refuse. Some people with swallowing difficulty still manage certain textures without issue, while struggling with others. A speech-language pathologist can formally assess swallowing and recommend specific modifications.
What’s the difference between normal aging and dementia-related appetite loss?
Normal aging causes gradual appetite decrease but the person remembers eating and can communicate preferences. Dementia causes more dramatic appetite loss, repeated asking for food despite recent meals, food refusal despite hunger signals, and loss of safety awareness around swallowing.
You Might Also Like
- How Speech Therapists Help With Dementia Eating Problems
- How Speech Therapists Help With Dementia Eating Problems
- How Poor Dental Health Can Affect Eating in Dementia
For more, see NIH MedlinePlus — dementia.