Reviewed by the Help Dementia Editorial Team — our editors review every article for accuracy against guidance from the National Institute on Aging, the Alzheimer’s Association, and peer-reviewed sources.
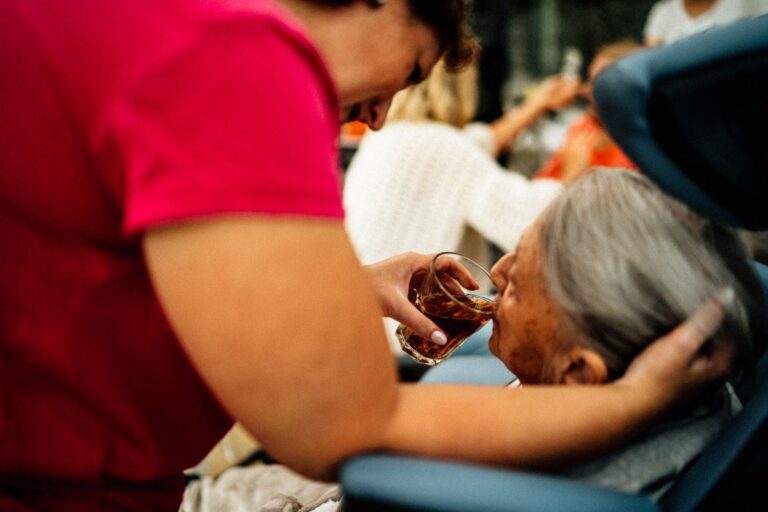
Speech-language pathologists, commonly called speech therapists, help people with dementia overcome eating and swallowing problems by assessing the underlying causes, designing safe eating strategies, and teaching caregivers how to prevent choking, aspiration, and malnutrition. These specialists evaluate how dementia has affected a person’s ability to chew, swallow, and manage food safely—skills that many people take for granted until neurological decline makes them difficult. For example, someone with mid-stage Alzheimer’s disease might suddenly refuse solid foods or cough while drinking water, signs that their swallowing reflex has weakened.
A speech therapist identifies exactly where and why the swallowing process is failing, then creates a plan to keep that person nourished and safe. Without professional assessment, families often guess at solutions, accidentally making things worse. A daughter might thicken her father’s water thinking she’s protecting him, only to learn from a speech therapist that his actual problem is weakness in his tongue, not his throat, and that thickened fluids might slow his swallow further. Speech therapists bring clinical testing, anatomical knowledge, and evidence-based techniques to a problem that is both medical and deeply personal.
Table of Contents
- What Causes Eating Difficulties in Dementia?
- How Speech Therapists Assess Swallowing Problems
- Modifying Food and Fluid Texture to Match Ability
- Teaching Proper Feeding Techniques and Positioning
- Recognizing Signs of Aspiration and When Professional Help Is Critical
- Supporting Families Through Diet Changes and Decision-Making
- The Role of Swallowing Exercises and Long-Term Adaptation
- Conclusion
- Frequently Asked Questions
What Causes Eating Difficulties in Dementia?
dementia damages the brain regions that control swallowing, chewing, and the coordination needed to move food safely from the mouth to the stomach. As neurons die, the brain loses its ability to signal the muscles involved in these movements. Additionally, dementia often brings secondary problems: people forget how to use utensils, lose interest in eating, become distracted during meals, or develop a texture preference that shifts unpredictably.
Some people with dementia retain the motor skill to swallow but lose the awareness that they should swallow—a dangerous situation where food or liquid sits in the mouth until they aspirate it into the lungs. The severity ranges widely. Someone in early dementia might struggle only with sticky foods like peanut butter or bread; someone in advanced dementia might have difficulty with both solid and liquid consistencies. Speech therapists recognize that eating problems in dementia are not simple appetite loss—they are symptoms of neurological damage that requires skilled diagnosis.

How Speech Therapists Assess Swallowing Problems
A speech therapist begins with a detailed history and observation: they watch the person eat, listen for coughing or throat clearing, ask about weight loss or repeated infections. They perform oral-motor tests, checking tongue strength, lip closure, and gag reflex. Some perform a more advanced test called a video fluoroscopic swallow study (VFSS), which uses X-ray video to show exactly where swallowed food or liquid is going—revealing whether it’s entering the airway, pooling in the throat, or moving normally.
This imaging test is the gold standard for understanding dysphagia, though it requires a trip to a hospital or imaging center and some cooperation from the person being tested. A major limitation of assessment in dementia is that people with advanced cognitive decline often cannot follow test instructions or hold still for imaging. A speech therapist must sometimes rely on indirect signs—watching for “silent aspiration,” where food goes into the lungs without the person coughing, which is especially dangerous because there’s no warning sign. This is why ongoing monitoring by caregivers is critical, and why a speech therapist teaches them what to watch for.
Modifying Food and Fluid Texture to Match Ability
One of the most direct interventions is changing the consistency of food and fluids. The National Dysphagia Diet establishes standardized texture levels: thin liquid (like water), nectar-thick (like applesauce), pudding-thick (like yogurt), and minced and moist foods for people who cannot manage regular solids. A person who coughs on regular water might drink nectar-thick liquid safely; someone who chokes on minced meat might tolerate pureed meat mixed with gravy. A speech therapist determines which level is safest and teaches caregivers to prepare or source foods at that consistency.
This works, but it has real tradeoffs. A spouse might feel grief watching their partner drink thickened juice that tastes noticeably different, or managing meals that look like baby food despite the person being cognitively aware enough to notice the change. Some people reject thickened liquids because the mouthfeel is unfamiliar, and forcing texture changes without buy-in can worsen eating refusal. A good speech therapist acknowledges this emotional dimension and helps families balance safety with dignity and preference.

Teaching Proper Feeding Techniques and Positioning
The way a person sits, how quickly they eat, and the size of bites they take all affect safety. A speech therapist teaches caregivers to seat the person upright at 90 degrees, ensure feet are flat on the floor, and allow adequate time—at least 20-30 minutes per meal, which is slower than most families are accustomed to. Small bites and frequent swallows reduce the amount of food in the mouth at one time, lowering aspiration risk. Some people benefit from turning their head slightly to one side while swallowing, which narrows the airway on that side and can redirect food away from the lungs.
These techniques require consistent practice and caregiver training. In a nursing home, a staff member might forget to ensure proper positioning, or a busy aide might feed someone too quickly. A speech therapist must follow up, observe, and retrain repeatedly. The burden on family caregivers at home is also significant: learning and remembering these techniques while managing other dementia care demands is exhausting, especially when the person being cared for doesn’t understand why things are being done differently.
Recognizing Signs of Aspiration and When Professional Help Is Critical
Aspiration—food or liquid entering the lungs instead of the stomach—is the main danger of eating problems in dementia. Some people cough visibly, but others aspirate silently, with no cough to warn that something has gone wrong. Over time, repeated aspiration can cause aspiration pneumonia, a serious infection that is a leading cause of death in advanced dementia. A speech therapist trains caregivers to recognize warning signs: coughing during or after swallowing, wet or gurgling voice quality, fever without other symptoms, or decline in eating ability.
However, even skilled observation misses silent aspiration. A person might seem fine at breakfast but have developed a lung infection by evening. This is why some families and care teams choose to pursue a video fluoroscopic swallow study despite the challenges—the certainty it provides about what’s actually happening during swallowing can guide decisions about diet level, medication options, or other interventions. A speech therapist helps interpret these results and adjust recommendations based on what the imaging shows.

Supporting Families Through Diet Changes and Decision-Making
A speech therapist doesn’t just prescribe a diet; they educate caregivers about why changes are necessary and help them navigate the emotional and practical sides of the change. They might suggest strategies like adding flavor and calories to thickened foods, finding commercial thickening products that taste better than older versions, or identifying preferred foods that naturally match the recommended texture. They also prepare families for the reality that as dementia progresses, texture tolerance might change again, requiring re-assessment and new strategies.
For example, a daughter working with a speech therapist learns that her mother’s weight loss and refusal to eat are signs of swallowing difficulty, not stubbornness. Understanding the root cause often shifts the conversation from frustration to problem-solving. The therapist might recommend high-calorie pureed foods, smaller and more frequent meals, or swallowing exercises that might slightly improve strength and coordination. This shifts the dynamic from trying to force someone to eat to finding ways that feel safe and manageable for everyone involved.
The Role of Swallowing Exercises and Long-Term Adaptation
Some speech therapists recommend swallowing exercises—movements designed to strengthen muscles or improve coordination. Exercises like tongue presses, head turns during swallowing, or the “Mendelsohn maneuver” (squeezing the throat during a swallow) show mixed results in dementia because many people cannot remember or follow the instructions. Unlike someone recovering from a stroke who can practice independently, a person with dementia might need to be reminded of the exercise every single time, making compliance impractical.
The longer-term outlook in dementia is progressive decline. A speech therapist helps families understand that interventions can slow complications and improve quality of life in the current stage, but the disease continues to damage the nervous system. The realistic goal is not to “cure” the eating problem but to maintain nutrition, prevent aspiration pneumonia, and preserve some enjoyment of eating for as long as possible. As dementia advances to its final stages, conversations may shift toward comfort care and the role of feeding tubes or reduced oral intake, topics a speech therapist can address alongside medical providers.
Conclusion
Speech therapists are essential members of the dementia care team, bringing expertise in swallowing physiology and practical knowledge about how to adapt eating and drinking to match a person’s abilities at each stage of decline. They assess what has broken, design solutions that balance safety with quality of life, and equip caregivers with the knowledge and techniques to prevent serious complications like aspiration pneumonia.
Without their involvement, families navigate eating problems through trial and error, often making things worse. If a family member with dementia shows signs of eating difficulties—coughing on water, weight loss, refusing meals, or wet voice quality—requesting a referral to a speech-language pathologist is a concrete step forward. The therapist’s assessment, recommendations, and ongoing support make the difference between a frustrating problem that spirals and a manageable situation where the person continues to eat safely, maintain nutrition, and retain some pleasure in meals.
Frequently Asked Questions
How often should a person with dementia see a speech therapist?
Initial evaluation is critical, followed by reassessment every 3-6 months or when eating ability changes. Many people benefit from monthly check-ins, though frequency depends on disease stage, available resources, and how quickly the person is declining.
Can swallowing exercises help someone with advanced dementia?
In most cases, no. Exercises require learning and memory that advanced dementia has impaired. A speech therapist focuses instead on texture modification and feeding techniques that don’t require the person to understand or remember instructions.
Is a feeding tube always necessary if eating becomes very difficult?
Not always. A feeding tube is one option, but it has its own risks and doesn’t eliminate aspiration entirely. A speech therapist, doctor, and family together can discuss whether a tube aligns with the person’s goals and quality of life. Some families choose to continue careful oral feeding even with higher aspiration risk, a legitimate choice when made with full information.
Can I thicken liquids at home, or do I need commercial products?
Cornstarch, flour, and gelatin can thicken liquids at home, but consistency is hard to control and texture can be gritty. Commercial thickeners are formulated for better taste and uniform texture. A speech therapist can recommend products and teach preparation.
What if my family member refuses to eat thickened foods or modified textures?
Refusal is common and meaningful. Work with the speech therapist to understand why—is it taste, appearance, texture feel, or a loss of interest in eating? Sometimes small changes (adding sweetness, different temperature, a favorite flavor) improve acceptance. Sometimes the person’s preferences have to be weighed against aspiration risk, a difficult conversation that a speech therapist can help facilitate.