
Reviewed by the Help Dementia Editorial Team — our editors review every article for accuracy against guidance from the National Institute on Aging, the Alzheimer’s Association, and peer-reviewed sources.
Frontotemporal dementia (FTD) primarily affects social behavior and personality by damaging the frontal and temporal lobes of the brain—the regions responsible for impulse control, decision-making, and understanding social cues. Unlike Alzheimer’s disease, which typically starts with memory loss, FTD often announces itself through dramatic shifts in how a person interacts with others: someone might become withdrawn and apathetic, or conversely, inappropriately disinhibited and impulsive. These behavioral changes happen before significant cognitive decline, making them both the earliest warning sign and the most disruptive consequence of the disease.
A person with FTD might stop greeting family members, neglect personal hygiene, or say hurtful things without apparent remorse or understanding of social impact. Consider a 58-year-old man who was known for his tact and consideration but gradually becomes socially inappropriate at work, making offensive comments and failing to maintain professional boundaries. He isn’t trying to be difficult—his brain’s social and emotional processing centers are deteriorating. Understanding these changes as a disease manifestation rather than a personality choice is essential for caregivers, family members, and the person with FTD themselves, particularly in the early stages when insight into the changes may still exist.
Table of Contents
- What Brain Changes Drive Social Behavior Problems in Frontotemporal Dementia?
- Behavioral Variants of Frontotemporal Dementia and Their Social Impact
- How FTD Affects Empathy and Emotional Recognition
- Managing Social Withdrawal and Behavioral Changes at Home
- Disinhibition and Socially Inappropriate Behavior
- Early Diagnosis and the Role of Personality Change as a Warning Sign
- Long-Term Support and Accepting the Trajectory of Change
- Conclusion
- Frequently Asked Questions
What Brain Changes Drive Social Behavior Problems in Frontotemporal Dementia?
The behavioral symptoms of FTD stem from selective degeneration in the prefrontal cortex, which governs judgment, empathy, and social awareness. This contrasts with Alzheimer’s disease, where damage begins in the hippocampus and gradually spreads, leaving social skills relatively intact until late stages. In FTD, a person may retain their factual knowledge and vocabulary while losing the ability to interpret a friend’s facial expression or understand why their behavior is hurtful.
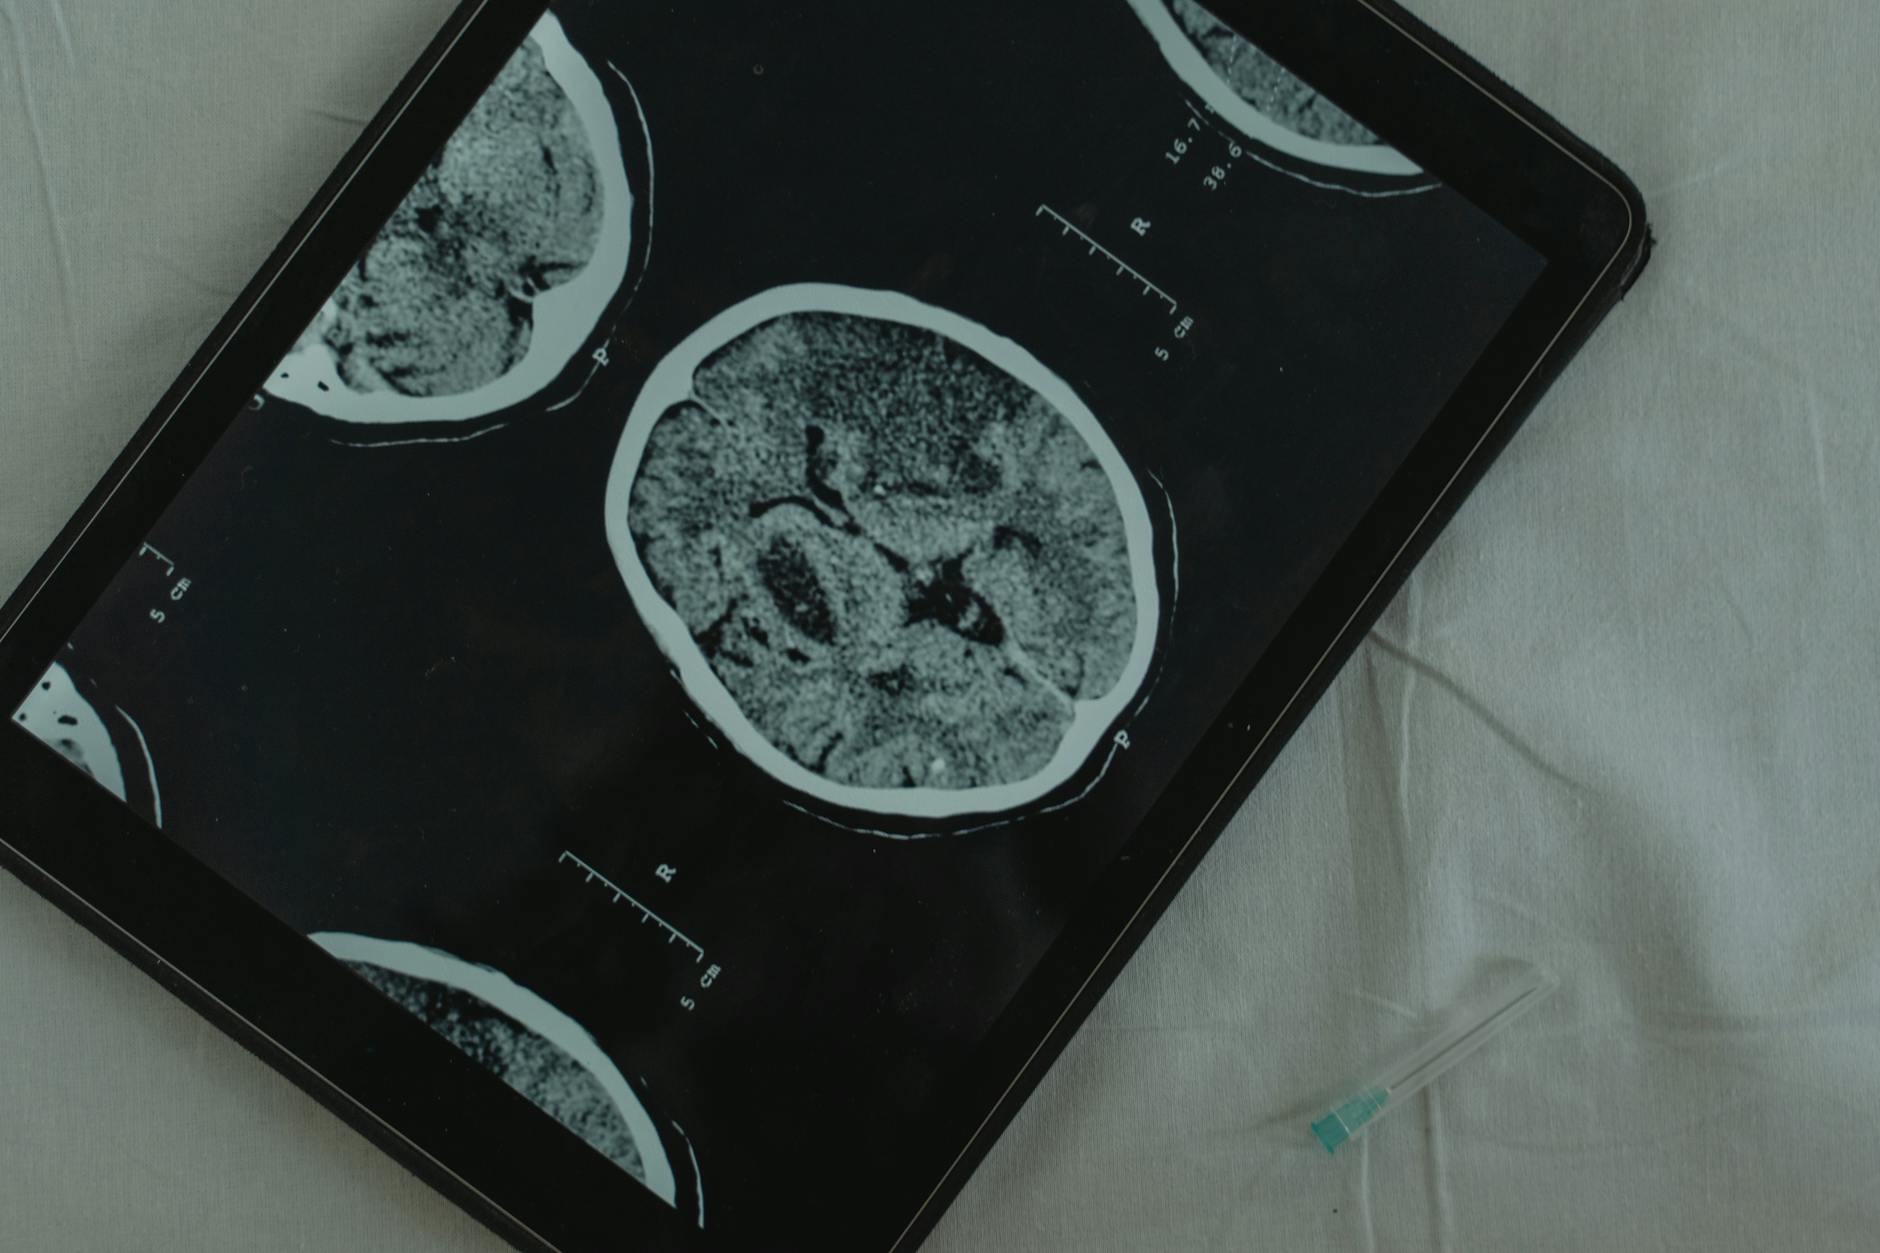
The orbitofrontal cortex, located just above the eye sockets, helps us weigh social and emotional consequences of our actions—when this area shrinks, decision-making becomes increasingly selfish and unfiltered. Neuroimaging studies show that atrophy in these frontal regions correlates directly with the severity of social withdrawal, lack of empathy, and behavioral disinhibition. A person with early FTD might still remember their children’s names and life events but fail to recognize when a family member is distressed. The emotional disconnect can be misinterpreted as coldness or cruelty, when in reality the person’s brain is no longer equipped to process and respond to emotional cues the way it once did.
Behavioral Variants of Frontotemporal Dementia and Their Social Impact
FTD presents in several behavioral patterns, each with distinct social consequences. The behavioral variant FTD (bvFTD) typically produces apathy, social withdrawal, or loss of empathy. A person might become completely indifferent to family events or refuse to participate in activities they once enjoyed. The primary progressive aphasia (PPA) variants, while primarily affecting language, can also disrupt social interactions as the person struggles to communicate and becomes frustrated or withdrawn.
Semantic dementia, a type of PPA, can make a person seem emotionally flat even though their comprehension and production of specific word meanings decline. One important limitation to understand: behavioral changes in early FTD can be mistaken for depression, midlife crisis, or deliberate rudeness, delaying diagnosis by months or years. A spouse might feel rejected when their partner stops initiating intimacy, or a workplace might discipline someone for inappropriate comments without realizing these are disease symptoms. This misattribution can create shame and conflict within the family before anyone recognizes that the brain itself has changed. Early recognition requires awareness that personality changes—especially when they represent a clear departure from someone’s lifelong character—warrant medical evaluation.
How FTD Affects Empathy and Emotional Recognition
One of the most painful aspects of FTD is the loss of empathy. A person with FTD may not understand why a family member is crying, may respond to bad news with inappropriate laughter or indifference, and may fail to recognize suffering in others. This isn’t callousness—it’s neurological damage to brain regions involved in emotional processing and theory of mind (the ability to understand others’ mental states). caregivers often describe this as watching a loved one “become a stranger.” The person appears unchanged in appearance and speech but acts as though they no longer care about the relationships that once defined them.
Consider a 62-year-old woman who was a devoted grandmother. As FTD progresses, she shows no interest in her grandchildren’s visits, doesn’t ask about their lives, and seems annoyed by their presence. She isn’t being deliberately hurtful—her anterior insula and amygdala, regions that process emotional empathy, are shrinking. Her family experiences this as abandonment, but the person with FTD isn’t making an emotional choice. This distinction matters profoundly for caregivers’ mental health and for the ability to maintain compassion as the disease progresses.

Managing Social Withdrawal and Behavioral Changes at Home
Caregivers face a significant tradeoff when responding to behavioral changes in FTD: direct confrontation often escalates agitation, but complete accommodation can enable harmful or inappropriate behavior. A more effective approach balances gentle redirection with acceptance of the disease process. If your loved one becomes socially withdrawn, forced participation in activities typically backfires, but structured, lower-pressure social contact—a short visit from one trusted person, a familiar activity done side-by-side—may engage them in ways that feel less threatening.
For inappropriate behavior or language, consequences don’t work because the person often lacks insight into why their behavior was wrong. Instead, caregivers can try redirecting attention, changing the environment, or using simple limits (“We don’t talk to people that way in this house”) without shame or punishment. Some families find that reducing overstimulation—too many people, too much noise—helps minimize behavioral escalation. It’s important to recognize that while you cannot restore the person’s old social awareness, you can structure their environment to prevent harm and maintain dignity.
Disinhibition and Socially Inappropriate Behavior
Behavioral disinhibition in FTD can manifest as sexual inappropriateness, offensive comments, poor table manners, or boundary violations. Unlike someone who has a lapse in judgment, a person with FTD may repeatedly display the same inappropriate behavior without learning or embarrassment. They might make comments about a person’s weight, appearance, or ability without understanding that this is hurtful. In social or family gatherings, this can be deeply distressing for the person with FTD’s loved ones and for others present.
A critical warning: disinhibited behavior sometimes escalates into aggression or dangerous decisions. A person with FTD might attempt to drive when unsafe, give away large sums of money, or engage in risky behavior without understanding the consequences. This requires active monitoring and, in some cases, restrictions on autonomy—a difficult conversation because the person with FTD may lack insight into their own impairment and resent being controlled. Early legal planning, such as establishing power of attorney while the person still has capacity, is essential for protecting both the person with FTD and the family.

Early Diagnosis and the Role of Personality Change as a Warning Sign
One reason FTD is often diagnosed late is that personality change doesn’t immediately suggest a brain disease. People often assume behavioral shifts are psychological, situational, or intentional. Yet personality change that represents a clear departure from the person’s lifelong character—introversion, extraversion, risk tolerance, moral values—is a significant red flag. If a cautious, ethical person becomes reckless and untrustworthy, or a social butterfly becomes withdrawn and indifferent, evaluation by a neurologist or neuropsychologist is warranted.
Diagnostic tools like the Frontotemporal Dementia Rating Scale (FRS) and neuropsychological testing can help identify the pattern of changes consistent with FTD. Brain imaging, including MRI and PET scans, may show atrophy in characteristic locations. Genetic testing is relevant for some families, as certain FTD cases are inherited (mutations in C9orf72, MAPT, or GRN genes). Early diagnosis doesn’t cure the disease, but it does allow families to make informed decisions about care, legal planning, and lifestyle adjustments while the person with FTD still has some insight into their condition.
Long-Term Support and Accepting the Trajectory of Change
FTD is progressive, meaning social and behavioral decline will continue. This reality requires caregivers and families to grieve the loss of the person as they were while adapting to who they are becoming. Support groups for FTD caregivers, many available through the Association for Frontotemporal Degeneration (AFTD), provide invaluable connection with others who understand the unique challenges of watching behavioral change without accompanying memory loss.
A spouse might need to grieve the end of their marriage as a partnership while still providing hands-on care. As FTD advances, behavioral symptoms often become less prominent as physical decline takes over—eventually, the person may become completely dependent for all activities. For some families, this later stage brings a kind of relief from the emotional strain of behavioral management, though it introduces new challenges around hygiene, nutrition, and comfort care. Understanding that FTD has a trajectory—that today’s crisis behaviors may eventually give way to physical dependency—can help caregivers plan for the long term and access appropriate level of care when home management becomes unsafe.
Conclusion
Frontotemporal dementia disrupts the social self in ways that are neurologically distinct from other dementias. The damage to the prefrontal and temporal regions responsible for empathy, impulse control, and social awareness means that behavioral and personality changes often precede memory loss and appear before other obvious cognitive decline. This pattern can make FTD difficult to diagnose and emotionally devastating for families, who may feel abandoned or hurt by changes that are actually the direct result of brain deterioration.
If you notice significant and sustained changes in personality, social engagement, or behavior in yourself or a loved one—especially when these changes contrast sharply with lifelong patterns—seek evaluation from a neurologist or memory specialist. Early diagnosis allows for legal and care planning while insight remains, connection with support resources, and honesty with the person about what is happening. FTD is a disease without a cure, but understanding its neurological basis allows caregivers to respond with compassion rather than blame, and to build a care plan that honors the person’s dignity through the stages ahead.
Frequently Asked Questions
Is social withdrawal in FTD the same as depression?
Not necessarily. While depression can occur alongside FTD and may contribute to withdrawal, FTD-related apathy is different—the person lacks motivation and interest without the sadness or hopelessness typical of depression. Neuropsychological testing and imaging can help distinguish between them, which matters because treatment approaches differ.
Can someone with FTD control their inappropriate behavior if they try hard?
Rarely. The brain regions responsible for inhibiting inappropriate responses are damaged. Trying harder or being shamed doesn’t fix the neurological problem and often increases frustration and agitation. Managing the environment and redirecting behavior are more effective than appeals to self-control.
How quickly does FTD progress?
FTD typically progresses over 7-13 years, but individual variation is significant. Some people decline more rapidly, while others plateau for periods. Behavioral and personality changes often progress faster than physical decline, meaning someone may seem cognitively intact while becoming increasingly behaviorally disabled.
Should I tell my loved one with FTD that they have the disease?
This depends on the person’s insight and the stage of disease. Early on, when insight is preserved, honesty (delivered sensitively) allows for planning and reduces confusion. As insight fades, repeatedly telling someone they have FTD can cause repeated grief. Discuss this with the care team and family to find an approach that respects the person’s dignity and stage of disease.
Are behavioral problems in FTD permanent?
They tend to progress and persist, but they can sometimes be managed or reduced through environmental changes, routine, and medication. The goal isn’t to cure the behavior but to maintain the person’s safety, dignity, and quality of life while managing the practical challenges these changes create.





