Injection training for the 2026 at-home Leqembi regimen teaches patients with mild cognitive impairment to give weekly shots at home after supervised practice. The gain is freedom from infusions, the limit is brain-swelling risk plus MRI checks, and the gap is thin direct proof on home starts.
Leqembi is lecanemab, an antibody drug for early Alzheimer's disease. Mild cognitive impairment means early, noticeable changes in memory or thinking that do not yet block daily life. Eisai and Biogen report the use covers adults with that stage or mild dementia due to Alzheimer's, with amyloid buildup confirmed by testing.
Medical information disclaimer: This article is for general educational purposes only and does not provide medical advice, diagnosis, or treatment. Always consult a physician or other qualified health professional about symptoms, medications, tests, or treatment decisions.
Table of Contents
- What the weekly home dose looks like
- Who can inject, and what training requires
- Why home start helps people with MCI
- What home dosing does not remove
- What to settle with your clinic first
What the weekly home dose looks like
The starting dose is 500 mg once weekly, given as two back-to-back 250-mg autoinjector shots of about 15 seconds each, according to the FDA approval announcement from Eisai and Biogen. Each shot goes under the skin, not into a vein. A care partner can give the shots when the patient cannot.
Eligible patients can now start lecanemab at home by self-injection. NeurologyLive reports the change removes the prior need for about 18 months of twice-monthly IV infusions before at-home maintenance in its report on the at-home starting dose. That shift cuts infusion visits but does not cut medical oversight. Home dosing still needs a prescription, amyloid confirmation, and a clinic safety plan.
Who can inject, and what training requires
Home use is not automatic after prescribing. Medicine Guide states patients or care partners may self-inject only after training and after a provider directly guides at least two straight doses and finds home use appropriate in its Leqembi drug guide.
The provider decides if technique, timing, and response are sound. Clinics often check these points before clearing solo shots:.
- adult with mild cognitive impairment or mild dementia due to Alzheimer's, plus confirmed amyloid
- completed device training for storage, skin site choice, full-dose delivery, and missed-dose rules
- two guided doses in a row with safe technique and no concerning reaction
- a named person to give or watch each dose when memory problems make steps hard
Why home start helps people with MCI
Travel is a real burden in early memory loss. Weekly shots at home replace long infusion appointments, waiting rooms, and IV placement. For working care partners and patients who tire easily, that saved time can protect rest and routine.
The effect estimate comes from bridging, not from a large home-start trial in MCI alone. NeurologyLive reports Phase 3 Clarity AD found IV lecanemab slowed worsening on CDR-SB by 27% at 18 months, while extension sub-studies showed weekly under-skin dosing gave equal drug exposure and similar amyloid removal. CDR-SB is a scale that tracks memory, judgment, and daily function. For MCI, the practical meaning is a slower decline for some patients, not restored memory.
What home dosing does not remove
Bleeding and swelling risk in the brain remains. The Optum and Eisai summary describes a boxed warning for ARIA, meaning brain swelling or tiny bleeds, for both IV and under-skin forms. ARIA means fluid or blood spots seen on MRI, often without symptoms. Risk for serious ARIA runs higher in people with two copies of ApoE e4, so guidelines call for a genetic-test talk before treatment.
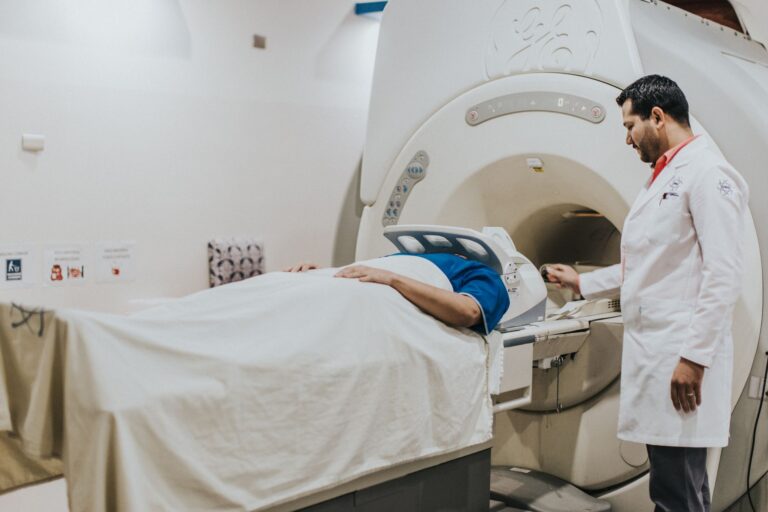
Monitoring still brings patients back to the clinic. The Medical Letter notes baseline brain MRI plus scheduled follow-up MRIs remain required because early ARIA is often silent in its assessment of the subcutaneous regimen. At-home shots do not replace those scans. A missed scan can leave swelling or bleeding undetected.
What to settle with your clinic first
Start with fit, not preference. Ask whether amyloid testing is complete, what the MRI dates will be, whether ApoE testing is advised, and who will watch the first two guided doses. Also ask what symptoms should pause dosing and trigger a call.
Make the home plan concrete before the first solo shot. Keep doses on the same weekday, store pens as directed, rotate skin sites, and log date, site, and any headache, confusion, dizziness, vision change, or nausea. Bring a list of who will give each weekly dose and who can drive to MRI visits.
You Might Also Like
- At-Home Leqembi vs IV Infusions After the 2026 FDA Decision: Benefits, Limits, and Evidence Gaps for People With Mild Cognitive Impairment
- MRI and ARIA Monitoring With At-Home Leqembi in 2026: Benefits, Limits, and Evidence Gaps for People With Mild Cognitive Impairment
- PrecivityAD2 Testing for Symptomatic Adults 40 and Older in 2026: What Changed and What Comes Next for People With Mild Cognitive Impairment