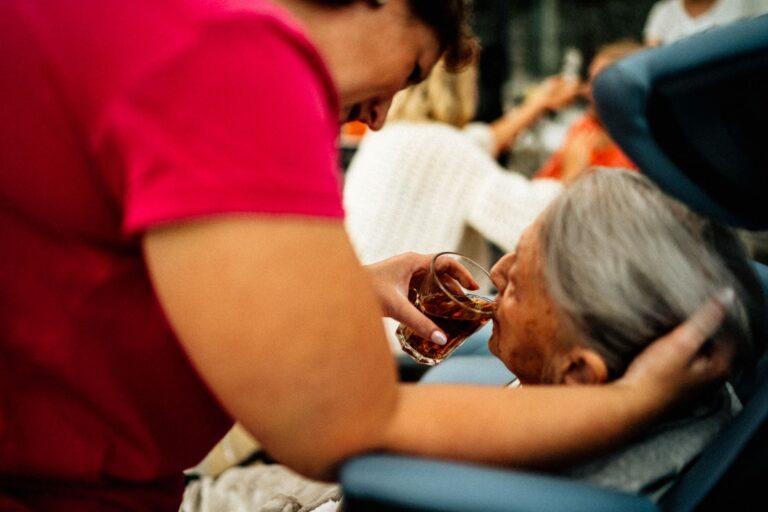
Yes, difficulty swallowing can be an early sign of dementia. It can start with subtle mouth and throat changes and then worsen as dementia progresses.
Doctors call impaired swallowing dysphagia, which covers holding food in the mouth, chewing, moving food back, and triggering the swallow. Early problems include coughing or choking, food sticking, longer meals, and a wet-sounding voice. Family members often miss these signs because many people with memory loss do not report swallowing problems.
Medical information disclaimer: This article is for general educational purposes only and does not provide medical advice, diagnosis, or treatment. Always consult a physician or other qualified health professional about symptoms, medications, tests, or treatment decisions.
Table of Contents
- What do early swallowing problems look like?
- Why does dementia disrupt swallowing?
- How common is it, and why does it matter?
- When should you seek help?
What do early swallowing problems look like?
Early change often sits in the mouth phase. Tongue movement weakens, food takes longer to move back, and the swallow reflex fires late. According to the Journal of Nutrition, Health and Aging review, these early oral-phase changes become more pronounced as dementia progresses rather than appearing only late (review of swallowing in dementia).
Watch for small shifts at meals. They may come and go before they form a clear pattern. These signs can stay mild for a time. In one memory-clinic barium-swallow study, 75% of Alzheimer's patients reported no swallowing complaints, which points to a continuum from silent difficulty to clear choking and swallowing apraxia.
- coughing or choking on food, fluids, or saliva
- food held in the cheeks or sticking in the throat
- much longer mealtimes
- wet or gurgly voice after swallowing
Why does dementia disrupt swallowing?
Dementia affects the brain signals that time a swallow. Throat sensation drops, tongue strength falls, mouth-to-throat transit slows, and the throat reflex responds late with weak clearance.
That poor timing breaks coordination. Food moves slowly, residue remains after a swallow, and the airway stays open too long. A person may pocket food, need repeat swallows, or cough during or after meals.
How common is it, and why does it matter?
Swallowing problems are very common as Alzheimer's disease advances. A systematic review in Dementia and Neuropsychologia estimated dysphagia prevalence of 84% to 93% in moderate-to-severe Alzheimer's disease, with instrumental testing finding far more cases than bedside checks alone (systematic review of dysphagia in Alzheimer's disease). Poor coordination lets food or drink enter the lungs instead of the stomach.
That event is called aspiration. It can bring chest infections, aspiration pneumonia, dehydration, malnutrition, weight loss, repeat hospital stays, and higher mortality. Risk rises when signs stay hidden. Silent difficulty can still allow small amounts of food or fluid to enter the airway, so a lack of complaints does not mean safe swallowing.
When should you seek help?
Treat new swallowing changes plus cognitive change as a reason to call a doctor. Difficulty swallowing alone cannot diagnose or predict dementia. Aging, stroke, Parkinson's disease, medicines, denture fit, and reflux can also cause it.
Ask for medical review when coughing or choking is new, chest infections repeat, weight falls, or meals take much longer. According to the Alzheimer's Society UK, these changes should prompt referral to speech-language therapy for swallowing assessment and diet or fluid changes (advice on speech-language therapy for swallowing). Bring clear notes to the visit. Record which foods or fluids trigger coughing, how long meals take, recent infections, and weight change.